
Are Spider Veins Dangerous? When Spider Veins Are Harmless — and When They Aren’t
Short answer: In most people, spider veins are harmless. They are very common, they rarely cause serious problems on their own, and they do not turn into blood clots. But spider veins are sometimes a visible clue to something underneath — reflux in a larger leg vein, or, in the case of a look-alike lesion called a spider angioma, a systemic condition such as liver disease. Two patterns deserve a medical evaluation rather than reassurance: a fan of tiny veins around the ankle or foot, and multiple spider-like lesions on the chest, face, or arms with a red dot at the center. Everything else is usually a question of comfort and appearance, not danger.
Medically reviewed by Obinna Nwobi, MD, board-certified vascular surgeon, Vein Health Clinics.
Seek emergency care now if you have
- Sudden shortness of breath, chest pain, coughing up blood, or a racing heartbeat — possible pulmonary embolism. Call 911.
- One leg that becomes swollen, warm, red, and painful over hours to days, especially in the calf — possible deep vein thrombosis. This needs same-day evaluation, not an appointment next month. See our warning signs of deep vein thrombosis.
- A vein that is bleeding and won’t stop. Lie down, elevate the leg above the level of your heart, and apply firm direct pressure. If bleeding continues, seek urgent care. Very thin-walled veins near the skin can bleed surprisingly heavily.
- An open sore or ulcer near the ankle that isn’t healing, or spreading redness with fever — evaluate promptly.
None of these are caused by spider veins themselves, but people often first notice them while worrying about visible veins.
First: are spider veins normal?
Yes — statistically, they’re the single most common finding in the venous system. In the population-based Bonn Vein Study of 3,072 adults, 59% of participants were classified as CEAP C1, the category for telangiectasias (spider veins) or reticular veins, when investigators assigned each person their highest clinical stage. Only 14.3% had varicose veins and under 1% had a healed or active ulcer.
So “I have spider veins” is closer to the norm than the exception. The useful question isn’t whether you have them, but whether anything else is going on.
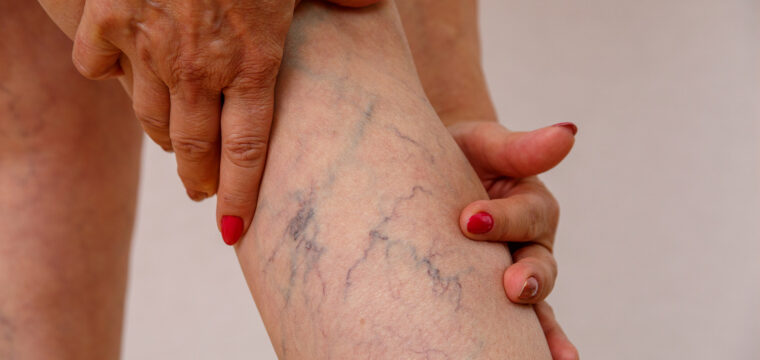
Spider veins — the medical term is telangiectasias — are tiny blood vessels within the skin, generally under about 1 mm across, that have become dilated and visible. They usually look red, blue, or purple, and often form a branching or web-like pattern. Reticular veins are the slightly larger, flat, bluish-green veins often seen alongside them.
Recognized contributors include:
- Family history — the strongest single factor most patients report
- Hormonal change — pregnancy, hormone therapy, menopause
- Age — visible telangiectasias accumulate over decades
- Prolonged standing or sitting, particularly occupational
- Higher body weight (see how your weight affects your veins)
- Local skin injury or previous procedures at the site
- On the face specifically, chronic sun exposure and rosacea are recognized contributors — this is a different situation from leg spider veins and is not treated the same way
When spider veins are genuinely worth a workup
There are three situations where visible small veins are a signal rather than a cosmetic issue.
- A fan of tiny veins around the ankle or foot (corona phlebectatica)
This specific pattern — fan-shaped intradermal telangiectasias on the inner, and sometimes outer, ankle and foot — is not treated as a minor finding. In the 2020 update to the CEAP classification, corona phlebectatica was added as clinical class C4c, placing it among the advanced skin signs of chronic venous disease rather than with ordinary spider veins. In a case-control study of patients with varicose veins, corona phlebectatica remained independently associated with venous ulceration (odds ratio 4.52, 95% CI 1.81–11.3) alongside lipodermatosclerosis and eczema.
What that means practically: it is a reason to have your deep and superficial leg veins imaged, not a reason to panic. It tells us to look for reflux and treat the underlying problem — which is exactly the scenario where treating early matters. It does not mean you have an ulcer or ever will.
This is the answer to “are spider veins on feet dangerous” and “spider veins on ankles”: location changes the meaning. Scattered spider veins on the thigh or calf carry a very different weight than a cluster at the ankle.
- Spider veins as a surface marker of reflux in bigger veins
Every vein in the leg is part of one connected system, and the pressure inside it is shared. When one-way valves in a larger vein such as the great saphenous vein stop closing properly, blood refluxes downward and pressure at the skin rises — and the smallest vessels are the ones that show it first.
The Edinburgh Vein Study, which examined a random population sample with duplex ultrasound, found a statistically significant trend for increasing venous incompetence with advancing grade of telangiectasia in the superficial veins (p = 0.006) and in the superficial-or-deep systems combined (p < 0.001). The association was real but, in the authors’ own words, “not wholly consistent” — telangiectasia grade did not track with deep-vein-only incompetence, and the small saphenous system showed no association.
The honest interpretation: more extensive spider veins raise the probability of underlying reflux; they do not establish it. Ultrasound is what settles it. And notably, this matters most when spider veins come with symptoms — aching, heaviness, swelling that worsens through the day, night cramps, itching over the veins. Spider veins alone rarely cause symptoms beyond mild itching or aching. Symptoms out of proportion to what you can see are the tell that something larger is refluxing underneath.
Important correction to something you’ll read online: spider veins are not a sign that you currently have a blood clot. The relationship runs the other direction — a previous deep vein thrombosis can damage valves and cause post-thrombotic venous hypertension, which can produce visible small veins years later. Spider veins don’t clot dangerously, and they don’t ulcerate.
- Spider angiomas — the look-alike that isn’t a vein problem at all
A spider angioma (also called spider nevus) is not a spider vein. It is a small central arteriole with fine vessels radiating outward, so it has a distinct red dot at the center and often a faintly reddened halo. Press it gently: a spider angioma typically blanches and then refills from the center outward. They favor the face, neck, upper chest, and arms — not usually the lower legs.
Spider angiomas matter because multiple lesions are associated with chronic liver disease. Here is the statistic stated correctly, because it is very often reported backwards: multiple spider angiomas have a specificity of about 95% for chronic liver disease — meaning they are uncommon in people who do not have it. That is not the same as saying 95% of people with spider angiomas have liver disease. Among patients who do have cirrhosis, the reported prevalence of spider angiomas is roughly 33%. Larger numbers of lesions correlate with more severe liver dysfunction.
At the same time, plenty of spider angiomas are entirely benign and physiologic:
- A solitary spider angioma is present in about 15% of young adults, usually fewer than three lesions
- They appear in roughly 60% of pregnancies and typically resolve after delivery
- They can appear with oral contraceptive use and often resolve when it stops
- They are also described with thyrotoxicosis and rheumatoid arthritis
So: one spider angioma on the cheek is a common, benign finding. Several new spider angiomas appearing on the chest or arms in an adult who isn’t pregnant is a reason to see a physician and have liver function evaluated — and that is an internal-medicine or hepatology question, not a vein procedure. This is the honest answer for anyone searching “liver spider veins” or “spider veins on chest”: if the lesions have a central red dot and sit on the upper body, they may not be a vein problem, and the right next step is bloodwork, not sclerotherapy.
When to worry about spider veins: a plain checklist
Get evaluated if any of these apply:
- A fan or cluster of tiny veins at the ankle or on the foot
- Spider veins accompanied by aching, heaviness, throbbing, or swelling that worsens as the day goes on
- Any skin change near the ankle — brown staining, hardening or tightening of the skin, eczema-like patches, or a healed or open sore
- Bulging, ropey veins visible alongside the spider veins (that’s C2 disease, not C1)
- Multiple spider-like lesions with a central red dot on the face, chest, or arms
- A previous DVT in that leg
- Rapid appearance of many new spider veins, or a spider vein that bleeds
You almost certainly don’t need urgent evaluation if your spider veins are scattered, symptomless, unchanged for years, and not at the ankle. Treatment then becomes a personal choice about comfort and appearance rather than a medical necessity.
What an evaluation actually involves
The essential point most articles skip: imaging comes before treatment. The 2022 European Society for Vascular Surgery clinical practice guidelines on chronic venous disease state that for patients presenting with reticular veins and/or telangiectasias, duplex ultrasound of the lower extremity veins should be performed before treatment to look for associated incompetent veins (Class I, Level C), and that significant associated incompetent veins should be treated first, before smaller veins are addressed (Class I, Level C).
That sequencing exists for a practical reason. If a refluxing truncal vein is feeding the surface network and you inject only what’s visible, the visible veins tend to come back. Duplex ultrasound is done standing, with reflux provoked, using a cut-off of greater than 0.5 seconds of reversed flow for superficial veins and greater than 1 second for the femoral and popliteal veins.
A complete visit typically includes your history and symptoms, an examination of both legs including the ankles, and a standing duplex ultrasound. That combination is what separates “cosmetic spider veins” from “surface sign of treatable venous disease” — and the two get very different treatment plans.
How spider veins are treated
When treatment is chosen, the guideline-supported options for small vessels are:
- Sclerotherapy — a sclerosing solution injected directly into the vessel, causing it to close and fade. The 2022 ESVS guidelines recommend sclerotherapy as first-choice treatment for reticular veins (Class I, Level A) and state it should be considered for telangiectasias (Class IIa, Level A). Read what to expect from sclerotherapy or see our sclerotherapy service page.
- Transcutaneous laser — should be considered for telangiectasias (Class IIa, Level B); often the better choice for very fine facial vessels.
- Treating the underlying reflux first where duplex ultrasound finds it — typically endovenous ablation of the incompetent truncal vein, after which the surface veins are addressed. If you’re weighing these against each other, see sclerotherapy vs. endovenous ablation.
Realistic expectations matter here. Treated vessels fade and close, usually over several weeks, and more than one session is common. New telangiectasias can still develop later, particularly with a strong family history or ongoing hormonal factors — treatment addresses the veins you have, not your tendency to form them. Temporary brownish discoloration, small trapped clots requiring drainage, and localized inflammation at injection sites are recognized side effects that should be discussed before you start.
Will insurance cover spider vein treatment?
Generally, no — treatment of telangiectasias on their own is considered cosmetic by Medicare and most commercial payers, and the Florida Medicare local coverage determination for varicose vein treatment explicitly excludes treatment of telangiectasia as cosmetic. However, if duplex ultrasound identifies significant reflux in a larger vein and you have documented symptoms, treatment of that problem may be covered when policy criteria are met. Vein Health Clinics publishes self-pay pricing for cosmetic and elective vein procedures — see our patient information page.
Frequently Asked Questions
What are spider veins?
Spider veins, medically called telangiectasias, are dilated blood vessels inside the skin, generally less than about 1 mm wide, that appear as red, blue, or purple lines in a branching or web-like pattern. They are classified as CEAP class C1 — the mildest category of chronic venous disorder.
Are spider veins dangerous?
On their own, no. Spider veins do not form dangerous blood clots, do not ulcerate, and rarely cause more than mild itching or aching. They become clinically important in three situations: when they form a fan at the ankle or foot, when they accompany symptoms or skin changes suggesting reflux in larger veins, or when the lesions are actually spider angiomas signaling a systemic condition.
Are spider veins normal?
Very. In the Bonn Vein Study of 3,072 adults, 59% were classified as C1 — telangiectasias or reticular veins — when each person was assigned their highest clinical stage.
What are spider veins a sign of?
Usually of genetics, hormones, age, and time spent upright. Sometimes they are a surface sign of venous reflux in a larger leg vein, which duplex ultrasound can confirm. If the lesions have a red dot at the center and sit on the face, chest, or arms, they may be spider angiomas, which can be associated with liver disease, pregnancy, or thyroid disorder.
What causes spider veins on the ankles, and are they dangerous?
Ankle telangiectasias generally reflect sustained high venous pressure at the lowest point of the leg. A fan-shaped cluster on the inner or outer ankle and foot is called corona phlebectatica, and in the 2020 CEAP classification it is graded C4c — an advanced sign of chronic venous disease. It warrants a duplex ultrasound. Contrary to what’s often written, footwear such as high heels or tight shoes is not an established cause of ankle spider veins.
What causes spider veins on the legs versus the face?
On the legs, the main drivers are heredity, hormonal change, prolonged standing, body weight, prior injury, and underlying venous reflux. On the face, chronic sun exposure and rosacea are recognized contributors — which is why facial vessels are often treated with laser rather than injection.
What causes spider veins on the chest?
Small visible vessels on the chest can be simple telangiectasias, but chest and upper-body lesions are also the classic location for spider angiomas. If they have a central red dot, radiate outward, and blanch when pressed, and especially if several have appeared recently, have a physician evaluate them rather than assuming they are a vein problem.
Do spider veins mean I have a blood clot?
No. The relationship runs the other way: a prior deep vein thrombosis can damage vein valves and raise venous pressure, which can later produce visible small veins. If one leg becomes suddenly swollen, warm, red, and painful, that is a possible DVT and needs same-day medical evaluation.
Is a spider angioma dangerous?
A single spider angioma is a common, benign finding — present in roughly 15% of young adults and about 60% of pregnancies. Multiple lesions carry about 95% specificity for chronic liver disease, meaning they are uncommon in people without it, and roughly a third of patients with cirrhosis have them. Several new lesions in a non-pregnant adult should prompt a medical evaluation including liver function testing.
When should I worry about spider veins?
Get evaluated for a cluster at the ankle or foot, aching or swelling that worsens through the day, brown staining or hardened skin near the ankle, an open or healed sore, ropey bulging veins alongside them, a previous DVT in that leg, a vein that bleeds, or multiple central-dot lesions on the upper body.
Can spider veins be removed permanently?
Treated vessels close and fade, typically over several weeks and often across more than one session. But treatment does not change your underlying tendency to form telangiectasias, so new ones can develop over time — particularly with a strong family history or ongoing hormonal factors. Anyone promising permanent elimination is overstating it.
Do I need an ultrasound before spider vein treatment?
The 2022 ESVS guidelines recommend duplex ultrasound before treating reticular veins or telangiectasias, to identify associated incompetent veins, and recommend treating significant incompetent veins first. Skipping that step is a common reason treated spider veins recur.
Have your veins looked at by a vascular surgeon.
Most spider veins are harmless — but the ones at your ankle, the ones that ache, and the ones with a red dot in the middle are worth a proper look. At Vein Health Clinics, Dr. Obinna Nwobi and our team evaluate both what you can see and what you can’t, with standing duplex ultrasound where it’s indicated.
We see patients at five Central Florida locations:
- Winter Haven — 1121 1st St S, Winter Haven, FL 33880 [VERIFY-7]
- Oviedo — 1000 Executive Dr, Suite 8, Oviedo, FL 32765 — 877-817-8346
- Winter Garden — 301 SW Crown Point Rd, Suite 140, Winter Garden, FL 34787 [VERIFY-7]
- Port St. Lucie — 1801 SE Hillmoor Dr, Suite C-208, Port St. Lucie, FL 34952 — 772-261-5116
- Ocala — 1830 SE 18th Ave, Suite 3, Ocala, FL 34471 — 352-690-6000
Request an appointment · Meet Dr. Nwobi
This article is for general education and is not a substitute for individual medical advice. If you have symptoms that concern you, please be evaluated.
Citations:
- Lurie F, Passman M, Meisner M, et al. The 2020 update of the CEAP classification system and reporting standards. J Vasc Surg Venous Lymphat Disord. 2020;8(3):342-352. doi:10.1016/j.jvsv.2019.12.075 — corona phlebectatica added as C4c; C1 = telangiectasias/reticular veins.
- Robertson L, Lee AJ, Gallagher K, et al. Risk factors for chronic ulceration in patients with varicose veins: a case control study. J Vasc Surg. 2009. PMID 19497512 — corona phlebectatica OR 4.52 (95% CI 1.81–11.3) for ulceration.
- Rabe E, Pannier-Fischer F, et al. Distribution and prevalence of reflux in the superficial and deep venous system in the general population — Bonn Vein Study, Germany. J Vasc Surg. 2008. PMID 18586443 — 59.0% C1; reflux threshold >500 ms.
- Ruckley CV, Allan PL, Evans CJ, Lee AJ, Fowkes FGR. Telangiectasia and venous reflux in the Edinburgh Vein Study. Phlebology. 2012;27(6). doi:10.1258/phleb.2011.011007 — trend of increasing superficial incompetence with telangiectasia grade (p = 0.006); no association with small saphenous system.
- De Maeseneer MG, Kakkos SK, Aherne T, et al. ESVS 2022 Clinical Practice Guidelines on the Management of Chronic Venous Disease of the Lower Limbs. Eur J Vasc Endovasc Surg. 2022. doi:10.1016/j.ejvs.2021.12.024 — duplex before treating C1 (I/C); treat incompetent veins first (I/C); sclerotherapy for reticular veins (I/A), for telangiectasias (IIa/A), transcutaneous laser (IIa/B); reflux cut-offs.
- Samant H, Kothadia JP, et al. Spider Angioma. StatPearls. NCBI Bookshelf NBK507818 — 95% specificity for chronic liver disease; ~33% prevalence in cirrhosis; solitary lesions in ~15% of young adults; ~60% of pregnancies.
- Li CP, Lee FY, Hwang SJ, et al. Spider angiomas in patients with liver cirrhosis: role of alcoholism and impaired liver function. Scand J Gastroenterol. 1999;34(5). doi:10.1080/003655299750026272 — 27 of 82 cirrhotic patients (33%) had spider angiomas.
- Gluud C, et al. / Cleveland Clinic Journal of Medicine 2022;89(6):301 — spider nevi in up to one-third of cirrhosis; lesion count correlates with disease severity.
- Uhl JF, Cornu-Thénard A, Carpentier PH, et al. Clinical and hemodynamic significance of corona phlebectatica in chronic venous disorders. J Vasc Surg. 2005. doi:10.1016/j.jvs.2005.08.031 — corona in 27.7% of an unselected CVD series; severity related to CEAP class, DVT history, and age.
- Medicare Local Coverage Determination L38720, Treatment of Varicose Veins of the Lower Extremities (First Coast Service Options, Jurisdiction N — Florida) — treatment of telangiectasia excluded as cosmetic

About The Author
Dr. Obinna Nwobi
Dr. Obinna Nwobi is a board certified vascular surgeon, who chose to practice in an underserved area in Florida. In a field that graduates only 100 new vascular surgeons a year, Dr. Nwobi is an exemplary vascular surgeon who worked for the Indian Health Services, Veterans Affairs Hospital, and large private and public hospitals.

Grab Our New Patient Offer
Free Consultation & Vein Screening
- Get a free venous ultrasound screening
- Free consultation with our vascular doctor to discuss your assessment results and treatment options
- Receive a personalized treatment plan
- Have all your questions answered
- Get advise on insurance and payment plans

Find Out if Your Are at
Risk of Vein Desease
This quick ONE MINUTE assessment can help you identify potential Vein Disease Symptoms.

At first I was hesitant to go there because I saw them thru an ad but I am so glad I did. I have gained so much knowledge and understanding about my fibroid and the options I have available to me. The nurse practitioner takes her time to answer all my questions and very competent. The staff is incredibly friendly and work with your schedule. I highly recommend this place

I am not a fan of Ultrasounds but the team that was responsible for assisting me were very professional and friendly. Once I was in the room, I can say that time went really fast. I sure recommend the clinic.




 Online Marketing For Doctors