
Medically reviewed by Obinna Nwobi, MD, board-certified vascular surgeon — Vein Health Clinics
The short answer
Smoking affects your circulation in three separate ways, on three different clocks:
- Within seconds to minutes — nicotine narrows small blood vessels. Measured directly, skin blood flow drops about 28–38% after a single cigarette, and forearm blood flow stays roughly 24% below baseline for at least 75 minutes after two cigarettes.
- Over hours — nicotine itself clears from your blood with a half-life of about 2 hours, but the vessel and blood-pressure effects outlast the drug.
- Over years — smoke damages the artery lining and drives plaque buildup (atherosclerosis), which is what causes peripheral artery disease, heart attack and stroke. That damage does not clear overnight.
And the question people search for most after those: no, smoking does not thin your blood. It does the opposite. Smoking raises fibrinogen, red-cell count and blood viscosity, and makes platelets stickier — so blood clots more readily, not less.
The good news is measurable too. Circulation begins improving within weeks of quitting, and the excess coronary heart disease risk caused by smoking falls by about half after one year without cigarettes.
How long does nicotine constrict your blood vessels?
Three different things are being asked here, and they have three different answers.
- How long does one cigarette’s vasoconstriction last? In laser-Doppler studies of skin microcirculation, a single cigarette cut cutaneous blood flow by 38.1% in habitual smokers and 28.1% in non-smokers, with recovery complete about 5 minutes later in smokers and 2 minutes in non-smokers (Clin Hemorheol Microcirc/PMID 9732157).
In a controlled forearm study, after two cigarettes (about 2.2 mg inhaled nicotine), forearm blood flow stayed significantly reduced — a maximal fall of 24% — for the full 75-minute follow-up, alongside a 34% rise in heart rate and a 17% rise in diastolic blood pressure (Eur J Clin Pharmacol, doi:10.1007/BF00314804).
So: the sharpest narrowing is over in minutes; the measurable reduction in limb blood flow persists for well over an hour after smoking.
- How long does nicotine stay in your body? Nicotine’s half-life in blood is roughly 2 hours; its metabolite cotinine persists far longer (on the order of 16 hours), which is why cotinine — not nicotine — is used to test for tobacco use. Clearance varies substantially between individuals and is slower with age.
- How long until my vessels behave normally again? That is the clock that matters clinically, and it is much longer than the drug’s. Repeated exposure produces endothelial dysfunction and arterial stiffening that persist between cigarettes. If you smoke a pack a day, your vessels never actually return to baseline during waking hours.
Does smoking thin your blood?
No. This is the most common misconception on this topic, and it is backwards.
Chronic smoking has been shown to produce a dose-related deterioration in blood rheology — higher haematocrit, higher plasma and whole-blood viscosity, higher fibrinogen, and increased red-cell aggregation, with the effect increasing across 10–20, 21–40 and 40+ cigarettes per day (Br J Haematol 1987, doi:10.1111/j.1365-2141.1987.tb04155.x). Importantly, that study also found the changes were reversible with abstention.
Thicker, more clot-prone blood shows up in outcomes. A meta-analysis of 32 observational studies covering nearly 4 million people found current smoking associated with a relative risk of about 1.17 for venous thromboembolism (DVT and pulmonary embolism), rising to ~1.30 after adjusting for body mass index (PLOS Medicine 2013, doi:10.1371/journal.pmed.1001515).
Is nicotine a blood thinner? No. Nicotine is a stimulant and a vasoconstrictor. Nothing in tobacco or in nicotine replacement acts as an anticoagulant. If you are on a prescribed blood thinner, smoking does not substitute for it and does not reduce your need for it.
⚠️ Important: do not stop or adjust any prescribed anticoagulant based on anything you read here. That is a conversation with your prescribing physician.
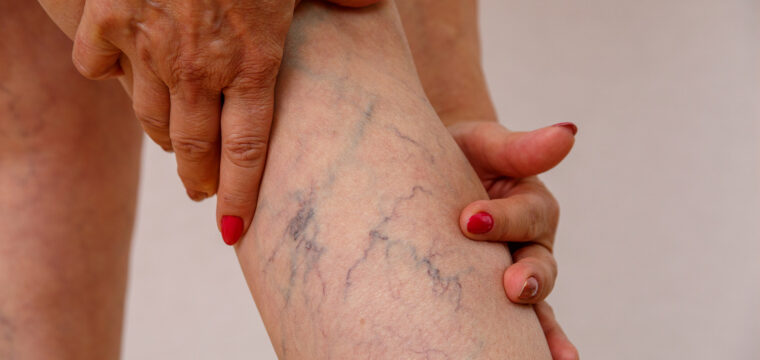
Does smoking cause varicose veins?
This deserves a straight answer rather than the usual hedge, because the evidence points in two directions and both parts are worth knowing.
- Population studies of the veins themselves found no link. The Edinburgh Vein Study duplex-scanned 1,566 randomly sampled adults and found no association between lifetime cigarette consumption and venous reflux in either sex (PMID 11511615). Height, obesity, pregnancy and straining at stool showed relationships; smoking did not.
- Genetic evidence points to a modest true effect. A two-sample Mendelian randomization study using UK Biobank (8,763 cases) and FinnGen (13,928 cases) found genetically predicted smoking initiation associated with varicose veins, OR 1.12 (95% CI 1.04–1.22) per standard deviation — smaller than BMI (OR 1.39) or height (OR 1.34), but present (JAHA 2021, doi:10.1161/JAHA.121.022286).
The honest summary: smoking is a weak contributor to varicose veins, not a primary cause. Genetics, height, pregnancy, standing occupations and body weight matter far more. What smoking does far more powerfully is damage your arteries — and worsen the consequences if you already have vein disease, because impaired circulation slows the healing of venous leg ulcers.
If someone tells you your varicose veins are “because you smoke,” that is an oversimplification. Quitting is still the highest-value thing you can do for your vascular health overall.
The part that is actually dangerous: your arteries
Vein problems are usually uncomfortable. Artery problems caused by smoking are limb- and life-threatening.
Smoking is a principal cause of peripheral artery disease (PAD) — narrowed arteries in the legs. In the 2024 multi-society ACC/AHA lower-extremity PAD guideline, smoking cessation is a core component of medical therapy for every patient with PAD (doi:10.1161/CIR.0000000000001251). The Surgeon General’s cessation findings are blunt on this point: cessation substantially reduces the risk of peripheral arterial occlusive disease, and among patients who already have PAD it improves exercise tolerance, reduces the risk of amputation after peripheral artery surgery, and increases overall survival.
Symptoms worth taking to a vascular specialist:
- Cramping or aching in the calf, thigh or buttock that starts when you walk and stops when you rest (claudication)
- Leg or foot pain at rest, especially at night, relieved by hanging the leg over the side of the bed
- A wound, sore or ulcer on the foot or lower leg that has not healed in two weeks
- One foot that is persistently cold, pale or blue compared with the other
The last three are features of chronic limb-threatening ischemia and warrant urgent vascular assessment, not a routine appointment.
🚑 When to go to the emergency room
Call 911 — do not drive yourself — for:
- Sudden face drooping, arm weakness, or slurred/garbled speech (stroke — note the time symptoms started)
- Chest pressure, pain or tightness, especially with sweating, nausea, or pain into the jaw or arm (heart attack)
- Sudden shortness of breath, sharp chest pain when breathing in, or coughing blood (possible pulmonary embolism)
- A leg or foot that is suddenly cold, numb, pale or painful (possible acute arterial occlusion — this is a time-critical limb emergency)
Go promptly, same-day, for a leg that becomes swollen, warm, red and painful — usually one leg — which may be a deep vein thrombosis. See our guide to the warning signs of deep vein thrombosis.
What about vaping, e-cigarettes and nicotine pouches?
The live evidence does not support treating these as circulation-neutral.
In a randomized, double-blind crossover trial, 22 healthy volunteers took 30 puffs of e-cigarette aerosol with and without nicotine. The nicotine-containing aerosol significantly increased both platelet thrombus formation and fibrin-rich thrombus formation at 15 minutes, and reduced microvascular dilatation capacity at 30 minutes. Aerosol without nicotine produced no comparable effect, identifying nicotine as the main driver (Cardiovascular Toxicology 2023, doi:10.1007/s12012-023-09802-9).
A separate head-to-head crossover study in 20 healthy young adults compared a combustible cigarette, e-cigarettes with and without nicotine, and chewing/nicotine bags. Every nicotine-containing product — including the pouch — significantly increased arterial stiffness parameters (Toxics 2023, 11:77).
What this means practically: switching from cigarettes to vaping or pouches is not the same as quitting, at least for your blood vessels. These are small, short-term studies in healthy young people, not long-term outcome trials, and they should not be read as saying vaping is equivalent to smoking — combustion products carry their own large burden. But “I only vape now” is not a reason to skip a vascular evaluation.
What actually changes when you quit
Based on the CDC and the 2020 Surgeon General’s report Smoking Cessation:
| Time after your last cigarette | What changes |
|---|---|
| ~20 minutes | Heart rate drops toward normal |
| ~12 hours | Carbon monoxide level in your blood returns to normal |
| 2 weeks – 3 months | Heart attack risk begins to drop; lung function begins to improve |
| 1–12 months | Coughing and shortness of breath decrease |
| ~1 year | Excess coronary heart disease risk is about half that of a continuing smoker |
| 2–5 years | Stroke risk may fall to about that of a person who never smoked |
| ~15 years | Coronary heart disease risk is close to that of a never-smoker |
Two honest caveats the internet usually omits:
- Existing plaque does not disappear. Quitting stops the ongoing injury and lets the artery lining recover function; it does not dissolve atherosclerosis that has already formed. Nothing you eat or drink “cleans out” your arteries.
- The blood-thickness changes are the reversible part. Viscosity, haematocrit and fibrinogen improve with abstention (Br J Haematol 1987) — which is why circulation improves noticeably in the first weeks even though the arteries take years.
How to help your circulation after quitting — the measures with real support are the same ones that treat vascular disease: regular walking (supervised exercise therapy is a first-line PAD treatment), blood pressure control, cholesterol management with a statin where indicated, diabetes control, and weight management. No supplement has been shown to reverse arterial narrowing.
Frequently asked questions
How long does nicotine constrict blood vessels? Sharp narrowing peaks within the first 2 minutes after a cigarette and eases within about 5 minutes in the skin, but reduced limb blood flow has been measured for at least 75 minutes after smoking. Nicotine itself has a blood half-life of roughly 2 hours.
Does nicotine thin your blood? No. Nicotine is a vasoconstrictor and a stimulant, not an anticoagulant. Smoking increases blood viscosity, fibrinogen and platelet stickiness, which makes clotting more likely.
Does smoking make your veins more visible? Not directly. Visible veins are driven mainly by low body fat, genetics, heat, exercise and — where they are bulging, ropey and symptomatic — by venous reflux. If prominent veins are new, painful, or accompanied by swelling, that warrants a duplex ultrasound rather than a lifestyle explanation. See why your veins become more visible when you lose weight.
How long after quitting smoking does blood flow increase? Acute nicotine-driven vasoconstriction resolves within hours of your last cigarette. Blood-rheology measures improve over weeks to months of abstention. Structural artery disease improves over years, and some of it does not reverse.
Can blood vessels heal after quitting smoking? Endothelial function — the lining’s ability to relax and dilate — improves after quitting. Established atherosclerotic plaque does not go away. Both statements are true simultaneously, and the second is the reason to be evaluated rather than to assume quitting has fixed the problem.
Does smoking cause varicose veins? Weakly, if at all. Duplex-based population data (Edinburgh Vein Study) found no association with venous reflux; genetic (Mendelian randomization) data found a modest association, OR 1.12. Body weight, height, pregnancy and family history are far stronger drivers.
Is vaping better for my circulation than smoking? Not neutral, and not a substitute for quitting. Nicotine-containing e-cigarette aerosol increased clot formation and reduced microvascular dilation within 15–30 minutes in a randomized crossover trial; nicotine pouches increased arterial stiffness in a separate study.
Get your circulation checked
If you smoke, have smoked, or have leg pain, swelling, cramping when you walk, or a sore that will not heal, a vascular evaluation is the right next step. Vein Health Clinics performs duplex ultrasound assessment of the leg arteries and veins and treats both venous disease and peripheral artery disease.
Vein Health Clinics — five Central Florida locations
| Location | Address | Phone |
|---|---|---|
| Winter Haven | 1121 1st St S, Winter Haven, FL 33880 | 877-817-8346 |
| Oviedo | 1000 Executive Dr, Ste 8, Oviedo, FL 32765 | 877-817-8346 |
| Winter Garden | 301 SW Crown Point Rd, Ste 140, Winter Garden, FL 34787 | 877-817-8346 |
| Port St. Lucie | 1801 SE Hillmoor Dr, Ste C-208, Port St. Lucie, FL 34952 | 877-817-8346 |
| Ocala | 1830 SE 18th Ave, Ste 3, Ocala, FL 34471 | 352-690-6000 |
Request a consultation · Meet Dr. Nwobi
This article is for general education and is not a substitute for individual medical advice. If you think you may be having a stroke, heart attack or pulmonary embolism, call 911.
Sources
- CDC, Benefits of Quitting Smoking — cdc.gov/tobacco/about/benefits-of-quitting.html; US DHHS, Smoking Cessation: A Report of the Surgeon General (2020); 1990 Surgeon General’s Report on Health Benefits of Smoking Cessation (MMWR summary).
- Peripheral haemodynamic effects of smoking in habitual smokers — doi:10.1007/BF00314804 (forearm blood flow −24%, sustained 75 min).
- Acute effect of smoking on cutaneous microcirculation — PMID 9732157 (−38.1% smokers / −28.1% non-smokers).
- Dose–effect relationship between smoking and blood rheology — Br J Haematol 1987, doi:10.1111/j.1365-2141.1987.tb04155.x.
- Current and Former Smoking and Risk for VTE: systematic review and meta-analysis — PLOS Med 2013, doi:10.1371/journal.pmed.1001515 (RR 1.17; 1.30 BMI-adjusted).
- Edinburgh Vein Study, lifestyle risk factors for venous reflux — PMID 11511615.
- Cardiometabolic, Lifestyle and Nutritional Factors in Relation to Varicose Veins: Mendelian Randomization — JAHA 2021, doi:10.1161/JAHA.121.022286.
- 2024 ACC/AHA multi-society Lower Extremity PAD Guideline — doi:10.1161/CIR.0000000000001251.
- E-cigarette vaping with nicotine causes increased thrombogenicity and impaired microvascular function — Cardiovasc Toxicol 2023, doi:10.1007/s12012-023-09802-9.
- Impact of chewing bags, e-cigarettes and combustible cigarettes on arterial stiffness — Toxics 2023;11:77.
- Nicotine pharmacology / pharmacokinetics — Benowitz & Jacob, in Clearing the Smoke (NCBI NBK222359).

About The Author
Dr. Obinna Nwobi
Dr. Obinna Nwobi is a board certified vascular surgeon, who chose to practice in an underserved area in Florida. In a field that graduates only 100 new vascular surgeons a year, Dr. Nwobi is an exemplary vascular surgeon who worked for the Indian Health Services, Veterans Affairs Hospital, and large private and public hospitals.

Grab Our New Patient Offer
Free Consultation & Vein Screening
- Get a free venous ultrasound screening
- Free consultation with our vascular doctor to discuss your assessment results and treatment options
- Receive a personalized treatment plan
- Have all your questions answered
- Get advise on insurance and payment plans

Find Out if Your Are at
Risk of Vein Desease
This quick ONE MINUTE assessment can help you identify potential Vein Disease Symptoms.

At first I was hesitant to go there because I saw them thru an ad but I am so glad I did. I have gained so much knowledge and understanding about my fibroid and the options I have available to me. The nurse practitioner takes her time to answer all my questions and very competent. The staff is incredibly friendly and work with your schedule. I highly recommend this place

I am not a fan of Ultrasounds but the team that was responsible for assisting me were very professional and friendly. Once I was in the room, I can say that time went really fast. I sure recommend the clinic.





 Online Marketing For Doctors