
How to Prevent Varicose Veins — and What You Can Actually Control
You can’t fully prevent varicose veins. The strongest risk factors — family history, age, sex, and height — aren’t things you can change. But you can lower your risk and slow the veins you already have. The measures with the best evidence behind them are: staying physically active, reaching and holding a healthy weight, and breaking up long stretches of sitting or standing with movement and leg elevation. Compression stockings help with aching and swelling, but there is no good evidence they stop varicose veins from forming. If you already have visible, bulging, or painful veins, prevention isn’t the right tool anymore — a duplex ultrasound evaluation is, because progression is treatable.
What varicose veins are, in one paragraph
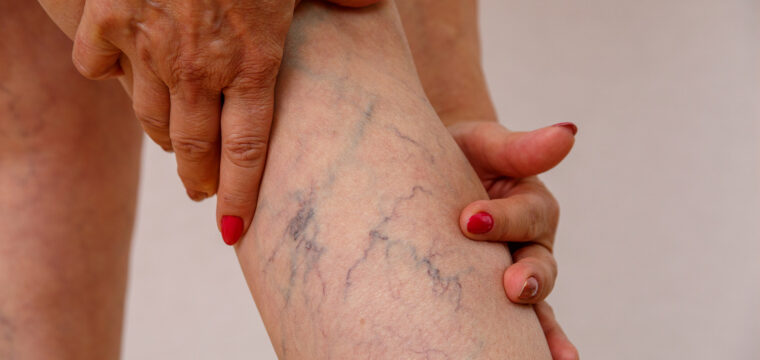
The veins in your legs move blood upward against gravity, and one-way valves inside them stop it from falling back down. When those valves or vein walls weaken, blood pools and flows backward — a process called reflux. The vein stretches, widens, and becomes the raised, rope-like vessel you can see at the skin surface. Clinically, a varicose vein is a dilated, tortuous superficial vein 3 mm or larger (StatPearls). This is common: an estimated 23% of US adults have varicose veins, and about 6% have more advanced chronic venous disease with skin changes or ulcers (SVS/AVF clinical practice guidelines).
The risk factors you can’t change
Being honest about this matters, because it’s why “prevention” has limits.
- Family history. One of the strongest risk factors for varicose veins (StatPearls; NHLBI).
- Age. Vein walls and valves lose elasticity over time.
- Sex. Varicose veins are more common in women, and the Framingham Study found a higher incidence in women than men (PMID 3395496).
- Pregnancy. Increased blood volume and pressure on the pelvic veins raise risk (NHLBI).
- Height. This one is newer and often surprises people. A UK Biobank study of nearly 500,000 adults found greater height independently associated with varicose veins (hazard ratio 1.74 comparing the tallest to the shortest quartile), and a Mendelian randomization analysis indicated the relationship is causal, not coincidental (Circulation 2018, PMID 30566020).
- Prior deep vein thrombosis (DVT). A history of clot damages valves and shows up as a risk factor in the same UK Biobank analysis.
If several of these apply to you, prevention shifts from “avoiding varicose veins” to watching for them early and treating them before they progress.
What actually lowers your risk — and slows what you already have
Move, and keep moving
This is the lever with the most consistent evidence. Walking and calf-muscle contraction operate the “muscle pump” that pushes venous blood back toward the heart. The Framingham Study found lower levels of physical activity in both men and women with varicose veins, and its authors concluded that increased physical activity and weight control may help prevent varicose veins in adults at high risk (PMID 3395496). For people who already have chronic venous disease, the 2022 European Society for Vascular Surgery guideline states that exercise should be considered to reduce venous symptoms (Class IIa, Level B).
Practical version:
- Walk daily if you can — it’s the single most vein-friendly form of exercise.
- If you sit or stand for work, move every 30–60 minutes, even briefly.
- Flex your ankles and calves while seated; it engages the same pump.
- Avoid heavy lifting because it causes varicose veins
Reach and hold a healthy weight
Excess body weight increases pressure inside the leg veins. Obesity appears as a risk factor in both the Framingham Study and the UK Biobank analysis, and NHLBI lists aiming for a healthy weight as a step that improves blood flow and eases pressure on the veins. Weight management won’t reverse veins that already exist, but it reduces the load driving further dilation.
How Your Weight Affects Your Veins
Break up long periods of sitting or standing
The Framingham Study found that women who spent eight or more hours a day sitting or standing had a significantly higher incidence of varicose veins than those spending four hours or fewer. NHLBI’s guidance is the same: avoid prolonged sitting or standing, elevate your feet when seated, and lie down with your feet above heart level for a few minutes several times a day to lower pressure inside the leg veins.
Don’t smoke
Smoking is not the dominant varicose vein risk factor, but the Framingham Study did find higher smoking rates among men with varicose veins, and smoking damages the vascular system broadly. There is no version of good leg-vein health that includes smoking.
How Smoking Affects Your Veins
During pregnancy
Pregnancy raises risk in ways you can’t avoid. Elevate your legs, avoid long stationary periods, and stay as active as your obstetric care team advises. Many pregnancy-related varicose veins improve in the months after delivery; those that don’t can be evaluated afterward.
How Pregnancy Affects Your Veins
Two things you’ll read online that the evidence doesn’t support
- “Eat more fiber to prevent varicose veins.” The theory — that constipation and straining raise abdominal pressure and dilate leg veins — dates to the 1950s and 60s and has been widely repeated ever since. When it was actually tested in a population, it didn’t hold. The Edinburgh Vein Study examined fiber intake, intestinal transit time, defecation frequency, and straining in 1,566 adults and concluded that an association between dietary fiber, constipation, and the presence or severity of varicose veins was not supported (PMID 11297893). The one exception: men who strained to begin a bowel movement had a higher risk of severe trunk varices (odds ratio 2.76). Eat fiber for your general health — just don’t count on it to protect your veins.
- “Wear compression stockings to prevent varicose veins.” Compression is genuinely useful for symptoms — aching, heaviness, swelling — and is a mainstay of conservative management. But as prevention, the evidence isn’t there. The Cochrane review of interventions for varicose veins and leg oedema in pregnancy found that compression stockings did not appear to have any advantages (CD001066.pub3). Use them to feel better, not to stop veins from forming.
When prevention is no longer the right question
If you can already see bulging or twisted veins, or your legs ache, throb, swell, cramp at night, itch, or feel heavy by the end of the day, you’re past the point where lifestyle change alone is the answer. Varicose veins are progressive in many people, and untreated chronic venous disease can advance to skin discoloration, hardening of the tissue around the ankle, and venous ulcers. The goal of treatment, in NHLBI’s words, is to relieve symptoms, keep varicose veins from worsening, improve appearance, and prevent serious complications such as ulcers and bleeding.
Evaluation starts with a duplex ultrasound to map which veins are refluxing. That’s what determines whether you need sclerotherapy, an endovenous ablation, or another approach — and it’s not something you can assess by looking at your legs.
Internal links: Varicose Vein Treatment · Spider Vein Treatment · Spotting the Warning Signs of Chronic Venous Insufficiency
When to seek urgent care
Prevention advice doesn’t apply to these situations. Seek medical care promptly if you have:
- Sudden swelling, pain, warmth, or redness in one leg — this can indicate a deep vein thrombosis (blood clot) and needs same-day evaluation.
- Chest pain, shortness of breath, or coughing up blood — call 911. These can be signs of a pulmonary embolism, a medical emergency.
- Bleeding from a varicose vein — lie down, elevate the leg above heart level, apply firm direct pressure, and seek care.
- An open sore or ulcer near the ankle that isn’t healing.
FAQs
Can varicose veins be prevented? Not completely. The strongest risk factors — family history, age, sex, height, and pregnancy — can’t be changed. What you can do is lower your risk with regular activity, a healthy weight, and avoiding long stretches of sitting or standing, and slow the progression of veins you already have.
How do I stop varicose veins from getting worse? Stay active so your calf muscle pump keeps working, manage your weight, elevate your legs above heart level for a few minutes several times a day, and break up prolonged sitting or standing. Compression stockings can ease aching and swelling. If the veins are already visible or symptomatic, get a duplex ultrasound evaluation — progression is treatable, and treatment is what prevents complications.
Does exercise prevent varicose veins? Physical activity is the measure with the most consistent evidence behind it. The Framingham Study found lower activity levels in people with varicose veins and concluded that more activity plus weight control may help prevent them in high-risk adults. Walking is ideal. Ask your provider about heavy lifting, which NHLBI notes may worsen existing varicose veins.
Do compression stockings prevent varicose veins? They help with symptoms like aching, heaviness, and swelling, but there’s no good evidence they prevent varicose veins from forming. A Cochrane review found compression stockings offered no clear advantage for varicose veins in pregnancy.
Does a high-fiber diet prevent varicose veins? Probably not. The Edinburgh Vein Study tested fiber intake, constipation, and straining in over 1,500 adults and found no supported association with the presence or severity of varicose veins. Fiber is good for you for other reasons.
Why am I getting varicose veins suddenly? Varicose veins usually develop gradually and become noticeable after a change — a pregnancy, weight gain, a new job with long hours on your feet, or simply age. Veins that appear rapidly, or one leg that swells suddenly and painfully, should be evaluated promptly to rule out a blood clot.
Concerned about the veins in your legs? Dr. Obinna Nwobi, MD, is a board-certified vascular surgeon who evaluates and treats varicose veins, spider veins, and chronic venous insufficiency at five Central Florida locations. Evaluation begins with a duplex ultrasound to identify exactly which veins are involved.
| Location | Address | Phone |
|---|---|---|
| Winter Haven | 1121 1st St S, Winter Haven, FL 33880 | 877-817-8346 ⚠️ |
| Oviedo | 1000 Executive Dr, Suite 8, Oviedo, FL 32765 | 877-817-8346 |
| Winter Garden | 301 SW Crown Point Rd, Suite 140, Winter Garden, FL 34787 | 877-817-8346 ⚠️ |
| Port St. Lucie | 1801 SE Hillmoor Dr, Suite C-208, Port St. Lucie, FL 34952 |
877-817-8346 |
| Ocala | 1830 SE 18th Ave, Suite 3, Ocala, FL 34471 | 352-690-6000 |
Request an appointment · Meet Dr. Nwobi
Citations
- NHLBI — Varicose Veins. nhlbi.nih.gov/health/varicose-veins — causes, risk factors, and lifestyle guidance including healthy weight, physical activity, avoiding prolonged sitting/standing, leg elevation, and the heavy-lifting caveat; treatment goal of preventing ulcers and bleeding.
- StatPearls — Varicose Veins, NCBI Bookshelf NBK470194 — definition as dilated tortuous superficial veins ≥3 mm; age and family history as important risk factors.
- SVS/AVF clinical practice guidelines, care of patients with varicose veins and associated chronic venous diseases — An estimated 23% of U.S. adults have varicose veins, while about 6% have more advanced chronic venous disease, according to the Society for Vascular Surgery and American Venous Forum’s 2011 clinical practice guideline.
- Framingham Study — Brand FN et al., “The epidemiology of varicose veins: the Framingham Study,” Am J Prev Med 1988;4(2):96–101, PMID 3395496, doi 10.1016/s0749-3797(18)31203-0 — 3,822 adults; lower physical activity and obesity in affected women, lower activity and higher smoking in affected men; ≥8 h/day sitting or standing associated with higher incidence in women; authors conclude activity and weight control may help prevent varicose veins in high-risk adults.
- UK Biobank / Mendelian randomization — Fukaya E et al., “Clinical and Genetic Determinants of Varicose Veins,” Circulation 2018;138(25):2869–2880, PMID 30566020, doi 10.1161/CIRCULATIONAHA.118.035584 — 493,519 individuals; confirms age, sex, obesity, pregnancy, prior DVT; height HR 1.74 (95% CI 1.51–2.01) upper vs lower quartile; MR odds ratio 1.26 supporting a causal role for height.
- Edinburgh Vein Study — “Fiber intake, constipation, and risk of varicose veins in the general population,” PMID 11297893 — 1,566 adults; association between fiber, constipation, and varicose veins not supported; straining in men OR 2.76 (95% CI 1.16–6.58) for severe trunk varices.
- Cochrane — “Interventions for varicose veins and leg oedema in pregnancy,” doi 10.1002/14651858.CD001066.pub3 — 7 trials, 326 women; compression stockings “do not appear to have any advantages.”
- ESVS 2022 clinical practice guidelines on chronic venous disease — “For patients with chronic venous disease, exercise should be considered to reduce venous symptoms” (Class IIa, Level B).

About The Author
Dr. Obinna Nwobi
Dr. Obinna Nwobi is a board certified vascular surgeon, who chose to practice in an underserved area in Florida. In a field that graduates only 100 new vascular surgeons a year, Dr. Nwobi is an exemplary vascular surgeon who worked for the Indian Health Services, Veterans Affairs Hospital, and large private and public hospitals.

Grab Our New Patient Offer
Free Consultation & Vein Screening
- Get a free venous ultrasound screening
- Free consultation with our vascular doctor to discuss your assessment results and treatment options
- Receive a personalized treatment plan
- Have all your questions answered
- Get advise on insurance and payment plans

Find Out if Your Are at
Risk of Vein Desease
This quick ONE MINUTE assessment can help you identify potential Vein Disease Symptoms.

At first I was hesitant to go there because I saw them thru an ad but I am so glad I did. I have gained so much knowledge and understanding about my fibroid and the options I have available to me. The nurse practitioner takes her time to answer all my questions and very competent. The staff is incredibly friendly and work with your schedule. I highly recommend this place

I am not a fan of Ultrasounds but the team that was responsible for assisting me were very professional and friendly. Once I was in the room, I can say that time went really fast. I sure recommend the clinic.





 Online Marketing For Doctors